
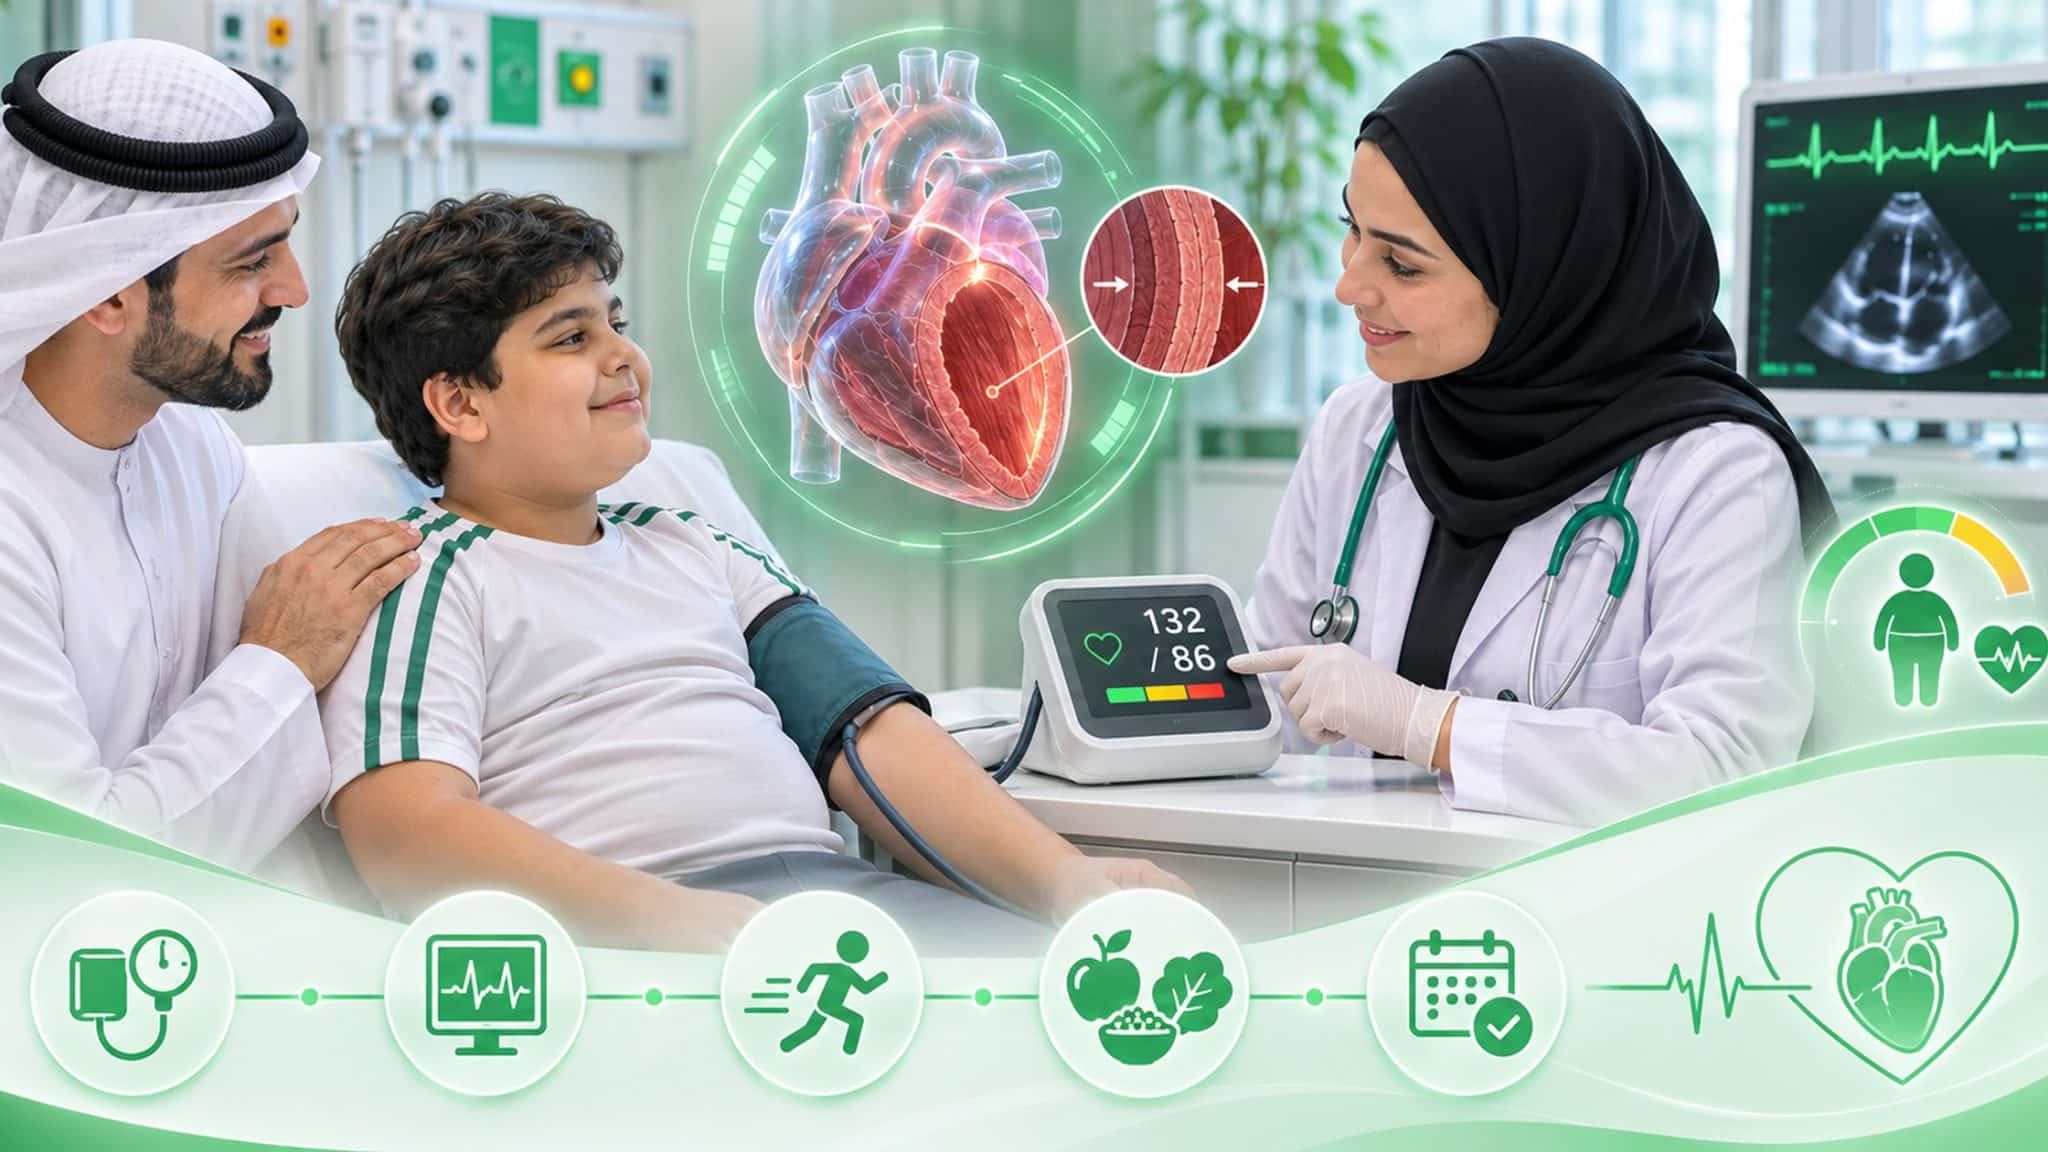
Blood pressure is usually the first sign
The heart’s earliest response to extra weight is rarely something a child feels. It shows up as a number.
A larger body means more blood vessels to fill and more tissue to supply. Excess weight also affects how the kidneys handle salt, how stiff the blood vessels become, and the hormones that regulate blood pressure. The result, in a meaningful share of children, is a reading that sits above where it should be for their age, sex and height.
The scale of this is larger than many parents expect. A study of children aged 3 to 12 seen in US primary care practices, published in Childhood Obesity in 2024, found that 31 percent of those with overweight or obesity had blood pressure above the normal range, including high blood pressure. The proportion climbed with weight: 27 percent among children with overweight, rising to 49 percent in the most severe category of obesity.
Children’s blood pressure has to be read against charts, not adult cutoffs. A reading that looks normal for a parent can be high for a ten-year-old. Our earlier post on hypertension risk in children explains how those charts work and which readings call for a second look.
What the heart itself does under extra load
When blood pressure stays high and the body is larger, the main pumping chamber of the heart, the left ventricle, has more work to do with every beat. Like any muscle asked to do more, it can thicken. In cardiology this is called left ventricular hypertrophy, and it can be measured on an echocardiogram.
In a child, this is usually a change in proportion rather than a dangerous finding on its own. What matters is the direction. A heart muscle that has thickened in response to a load can often return toward normal when the load comes off. A heart that keeps working against high pressure for decades is a different story, and that is the trajectory pediatric cardiologists want to change early.
Other changes tend to travel alongside. Cholesterol and triglyceride levels are more often abnormal. The body may become less responsive to insulin, an early step toward type 2 diabetes. Fat can build up in the liver as well, a condition now called metabolic dysfunction-associated steatotic liver disease, which shares many of the same drivers as the heart changes. In some children, the lining of the arteries already shows the first signs of stiffening, years before any of it would matter in a symptom sense.
Breathlessness is a common worry. A child carrying extra weight who tires quickly in PE is far more often out of condition than showing signs of heart disease, and fitness usually improves quickly with regular activity. Breathlessness that seems out of proportion, that comes with chest pain, dizziness or fainting, or that appears at rest is different, and should be assessed rather than put down to weight.
None of this is inevitable, and none of it is a diagnosis for any particular child. It is the reason a cardiologist takes a careful look rather than waiting.
Sleep, breathing and the heart
One link parents often miss runs through the night. Children carrying extra weight are more likely to have obstructive sleep apnea: repeated pauses or narrowing of the airway during sleep, often with loud snoring, restless sleep, gasping, or night sweats.
Each pause briefly lowers oxygen and raises the heart rate and blood pressure. Over months and years, untreated sleep apnea can add to blood pressure problems and place extra strain on the right side of the heart.
It also shows up in the daytime as tiredness, irritability, poor concentration and morning headaches, which are easy to attribute to a late bedtime or too much screen time. A child who snores most nights, especially with pauses, is worth mentioning to the pediatrician, who may arrange an assessment. Treatment, which sometimes means removing enlarged tonsils and adenoids, often improves sleep and can help blood pressure too.
What a cardiology assessment involves
A referral to cardiology for weight-related concerns is not a referral for a lecture. The visit is about measuring accurately and understanding what, if anything, the heart is already showing.
A typical assessment includes:
- Repeated blood pressure readings using a cuff sized for the child’s arm
- A review of family history, particularly early heart disease, high blood pressure, diabetes or high cholesterol
- An ECG to check rhythm and look for signs of thickened heart muscle
- An echocardiogram when blood pressure is persistently high, to measure the heart walls and assess function
- Sometimes 24-hour ambulatory blood pressure monitoring, to separate true high blood pressure from readings raised by clinic nerves
- Coordination with blood tests for cholesterol, blood sugar and liver function, often arranged with the pediatrician
At our Dubai Healthcare City clinic, a first visit usually takes about an hour, much of it spent talking rather than testing. Children are encouraged to ask their own questions, and many are curious to see their heart moving on the echo screen.
The cuff size point deserves emphasis. A cuff that is too small for a child’s arm can make blood pressure read higher than it truly is, which is one of the reasons repeat readings in a specialist setting matter. Our hypertension and cholesterol clinics are set up for this kind of careful measurement and follow-up.
The language that helps
How weight is discussed with a child matters almost as much as the numbers. Children who feel judged about their bodies often eat less in front of others and more in private, and avoid the very activities that would help.
Cardiologists and pediatricians who work with families on this tend to talk about the heart, strength, energy and sleep rather than about size or appearance. The goal is framed as the whole family eating and moving in ways that help everyone’s heart, not as a diet for one child. Siblings, parents and grandparents all benefit, and the child is not singled out at the dinner table.
Small habits around language carry weight too. Praising effort, such as a walk taken or a new vegetable tried, works better than praising a number on the scale. Weighing is best left to clinic visits rather than done at home, where it can turn a health goal into a daily source of worry.
Practical changes are usually modest and steady: fewer sugary drinks, more water, regular family meals, less time sitting, more time moving in ways the child actually enjoys. In Dubai and across the UAE, the cooler months from November to March open up evening walks, cycling tracks and beach afternoons that are harder to fit into the summer. Our nutrition counseling service works with families on the food side in detail, and our earlier post on preventing childhood obesity covers the broader prevention picture.
Where the numbers can go from here
Back to the ten-year-old with the reading of 124 over 82. In a child, that number is not a verdict. It is a starting point, measured early enough that a lot can still change.
Children’s hearts and blood vessels respond well when the load eases. Blood pressure can come down with steady changes in activity, sleep and diet, sometimes within months. A heart wall that had begun to thicken can settle. When medication is needed, it is used alongside those changes, not instead of them, and reviewed regularly.
A year later, the same child might have a reading in the normal range, a heart that looks ordinary on the echo, and a family that walks together on cool evenings without thinking of it as treatment. That is a realistic outcome, not a best case.
The cardiology role is to measure well, explain clearly, and keep checking the direction of travel. For families in Dubai, follow-up visits are usually spaced every few months at first, then less often as the numbers settle. Our Dubai Healthcare City team, with colleagues in Abu Dhabi and Al Ain, follows children through that process, and a first assessment can be arranged through our appointments page.
Consultant, Fetal & Pediatric Cardiologist – American Board
Assistant professor, Columbia University, New York
Pediatric Cardiac Surgeon – American Board 

Dr. Mohamed Sulaiman

Dr. Emile A. Bacha