
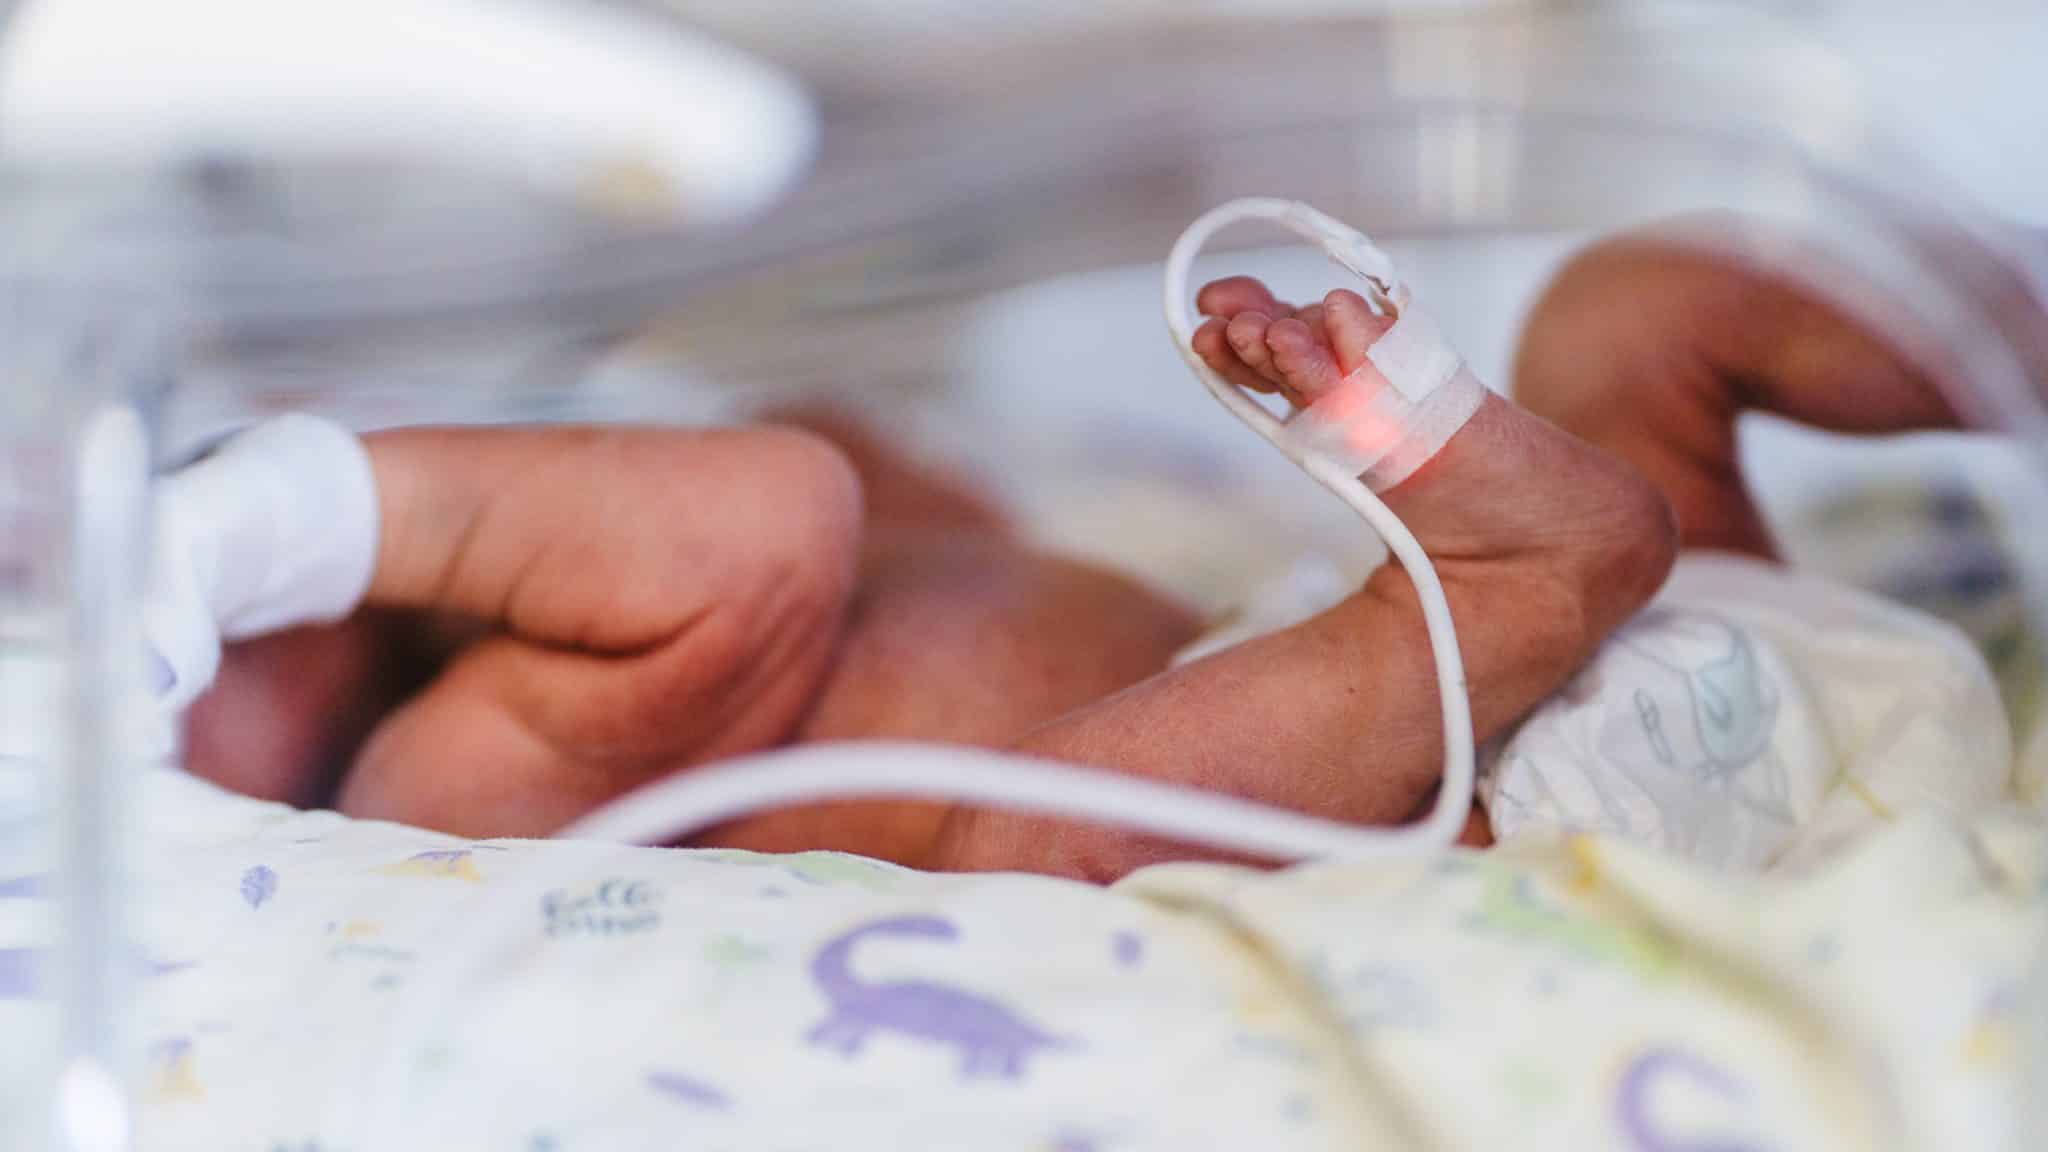
Born at 30 weeks, weighing 1.4 kg. Nine months later, she sits on her mother’s lap at a well-baby visit, and the growth chart says she is near the bottom of the curve. A neighbor’s baby, born the same week at full term, is crawling and pulling to stand. She is just starting to sit without support.
Then the pediatrician does a quick calculation and plots the dot again, ten weeks to the left. The same weight now sits comfortably in the middle of the chart. The sitting looks right on time.
That calculation is called corrected age, and for families of babies born early, it changes how almost every number in the first two years should be read. Our General Pediatrics team follows premature babies through this period at our Abu Dhabi branches in Al Karamah and MBZ and at The Heart Medical Center in Al Ain, with pediatric care also available at our Dubai Healthcare City branch.
Prematurity is more common than many parents assume
A baby is considered premature, or preterm, when born before 37 weeks of pregnancy. According to the CDC, preterm birth affected about 1 in every 10 babies born in the United States in 2022.
Most of those babies are born only a few weeks early. A smaller number arrive much earlier and spend weeks or months in a neonatal unit. Each group has a different starting point, but the questions families bring home are often the same. Is she growing enough? Is he behind? When will they catch up?
World Prematurity Day, on November 17, is a reminder that these questions are shared by a great many families, and that the answers are usually more encouraging than the first chart suggests.
How corrected age works
Corrected age is a baby’s age counted from the due date rather than the birth date. The calculation is simple: take the baby’s actual age, then subtract the number of weeks they were born early.
A baby born at 30 weeks arrived 10 weeks before the 40-week due date. At nine months old, her corrected age is roughly six and a half months. That is the age her growth and development should be compared against.
The correction matters for babies born only a little early too. A baby born at 35 weeks is five weeks premature. At four months old, that baby’s corrected age is under three months, and expecting four-month skills, such as rolling or reaching steadily for toys, would be expecting too much too soon.
The American Academy of Pediatrics advises using corrected age for growth and milestones through the first two years. By then, most of the gap has narrowed enough that the correction no longer changes the picture much.
There is one important exception. Vaccines are given by actual age from birth, not corrected age, unless the baby’s doctor advises otherwise for a specific reason. Premature babies need protection from infections on the same schedule as other babies, and often more so.
What catch-up growth usually looks like
Catch-up growth is the faster-than-usual growth that lets many premature babies move closer to the curves of babies born at term. It does not happen all at once, and it does not happen evenly.
Head size tends to catch up first, often within the first months after discharge. Weight usually follows, and length tends to take longest. Many babies born early move steadily toward the middle ranges over the first few years, though some remain on the smaller side, especially if they were small for their gestational age at birth or had a long or complicated neonatal stay.
What pediatricians watch most closely is the direction of the line, not where it sits. A baby following their own curve, even a low one, is usually doing well. Family build plays a part as well. Two parents of modest height are likely to have a child who settles on a lower centile, whether born early or not, and that is healthy for them. A baby whose line flattens, or crosses downward through the curves, needs a closer look. Our earlier post on understanding growth charts explains how to read those lines in more detail.
Families should also expect premature babies to be plotted on different charts at different stages. In the neonatal unit, specialized charts designed for preterm babies are used. After discharge, the standard infant growth charts take over, with the dots placed at corrected age.
Feeding for growth without overdoing it
Feeding is where most of the day-to-day effort goes. Many premature babies go home on fortified breast milk or a special formula with extra calories and nutrients, and some need iron or vitamin D supplements. These choices are made by the neonatal team and pediatrician based on the baby’s weight, blood tests and how they are feeding, and they change as the baby grows.
The goal is steady, proportionate growth. More is not always better. Rapid weight gain far beyond length gain is not the aim, and pediatricians look at weight, length and head size together for that reason.
In the early weeks at home, some babies need waking for feeds on a schedule set by the neonatal team, because small babies may not wake reliably when hungry. That schedule is usually relaxed as weight gain becomes steady. Reflux, with frequent spitting up, is also common in premature babies. Most of it is a laundry problem rather than a medical one, but reflux that comes with poor weight gain, pain or breathing difficulty should be reviewed.
Solid foods are usually introduced around six months of corrected age, not actual age, once the baby shows readiness: good head control, sitting with support, and interest in food. Some premature babies take longer to accept textures, particularly if they had long periods of tube feeding. That is common and usually improves with patient, gradual exposure.
When feeding is a struggle, or weight gain is slow despite good effort, our nutrition counseling service works alongside the pediatrician to adjust the plan.
What the pediatrician checks at each visit
Premature babies usually have more frequent check-ups in the first year than babies born at term. At our Abu Dhabi and Al Ain clinics, those infant wellness checks cover a broader list than routine visits. They typically include:
- Weight, length and head circumference, plotted at corrected age
- Feeding history, including volumes, frequency and any difficulty
- Development compared with corrected-age milestones
- Vision and hearing follow-up, as advised after the neonatal stay
- Vaccine schedule by actual age, including seasonal protection where recommended
- Review of any ongoing issues from the neonatal stay, such as breathing, heart or eye follow-up
Many parents arrive at the first visit after discharge with a notebook of feed times, volumes and diaper counts. It is worth bringing, since a week of real numbers says more than any single weight on the clinic scale. Bringing the neonatal discharge summary helps a great deal too. It records the baby’s birth weight, gestational age, any complications and the feeding plan, and it saves the pediatrician piecing those details together from memory.
Development deserves its own attention. Corrected age applies to milestones such as smiling, sitting, crawling and first words, just as it does to weight. Most premature babies meet their milestones on time when measured that way. Some need extra support with movement, feeding or speech, and early help makes the most difference. Where there are concerns, our Pediatric Neurodevelopment team can carry out a fuller developmental assessment.
Signs worth raising before the next visit
Most growth concerns can wait for the next scheduled check. A few cannot. A baby who has not gained weight for two weeks, is having noticeably fewer wet diapers, or is becoming less interested in feeds should be seen sooner. So should a baby who breathes fast at rest, sweats or tires during feeds, or looks pale or blue around the lips, since these can point to heart or breathing problems that sometimes accompany prematurity. Where a heart question arises, the pediatrician can coordinate with our pediatric cardiology team, which is based mainly at Dubai Healthcare City and also sees babies in Abu Dhabi and Al Ain.
Fever in a baby under three months of age, counted by actual age, always needs prompt medical assessment.
The dot on the chart
The nine-month-old from the beginning of this post did not change between the first plot and the second. Only the way her age was counted did. That shift, from the birth date to the due date, is often the moment a parent’s shoulders drop a little.
Corrected age will not answer every question. It does make the questions fairer, and it gives a premature baby the time they were owed before anyone starts comparing. Families in Abu Dhabi and Al Ain who want help reading their baby’s chart, or planning the first year after the neonatal unit, can reach our pediatricians through the KidsHeart contact page.


Dr. Eslam El-Baroudy
Prof. Consultant of Pediatrics Faculty of Medicine Department of Health