
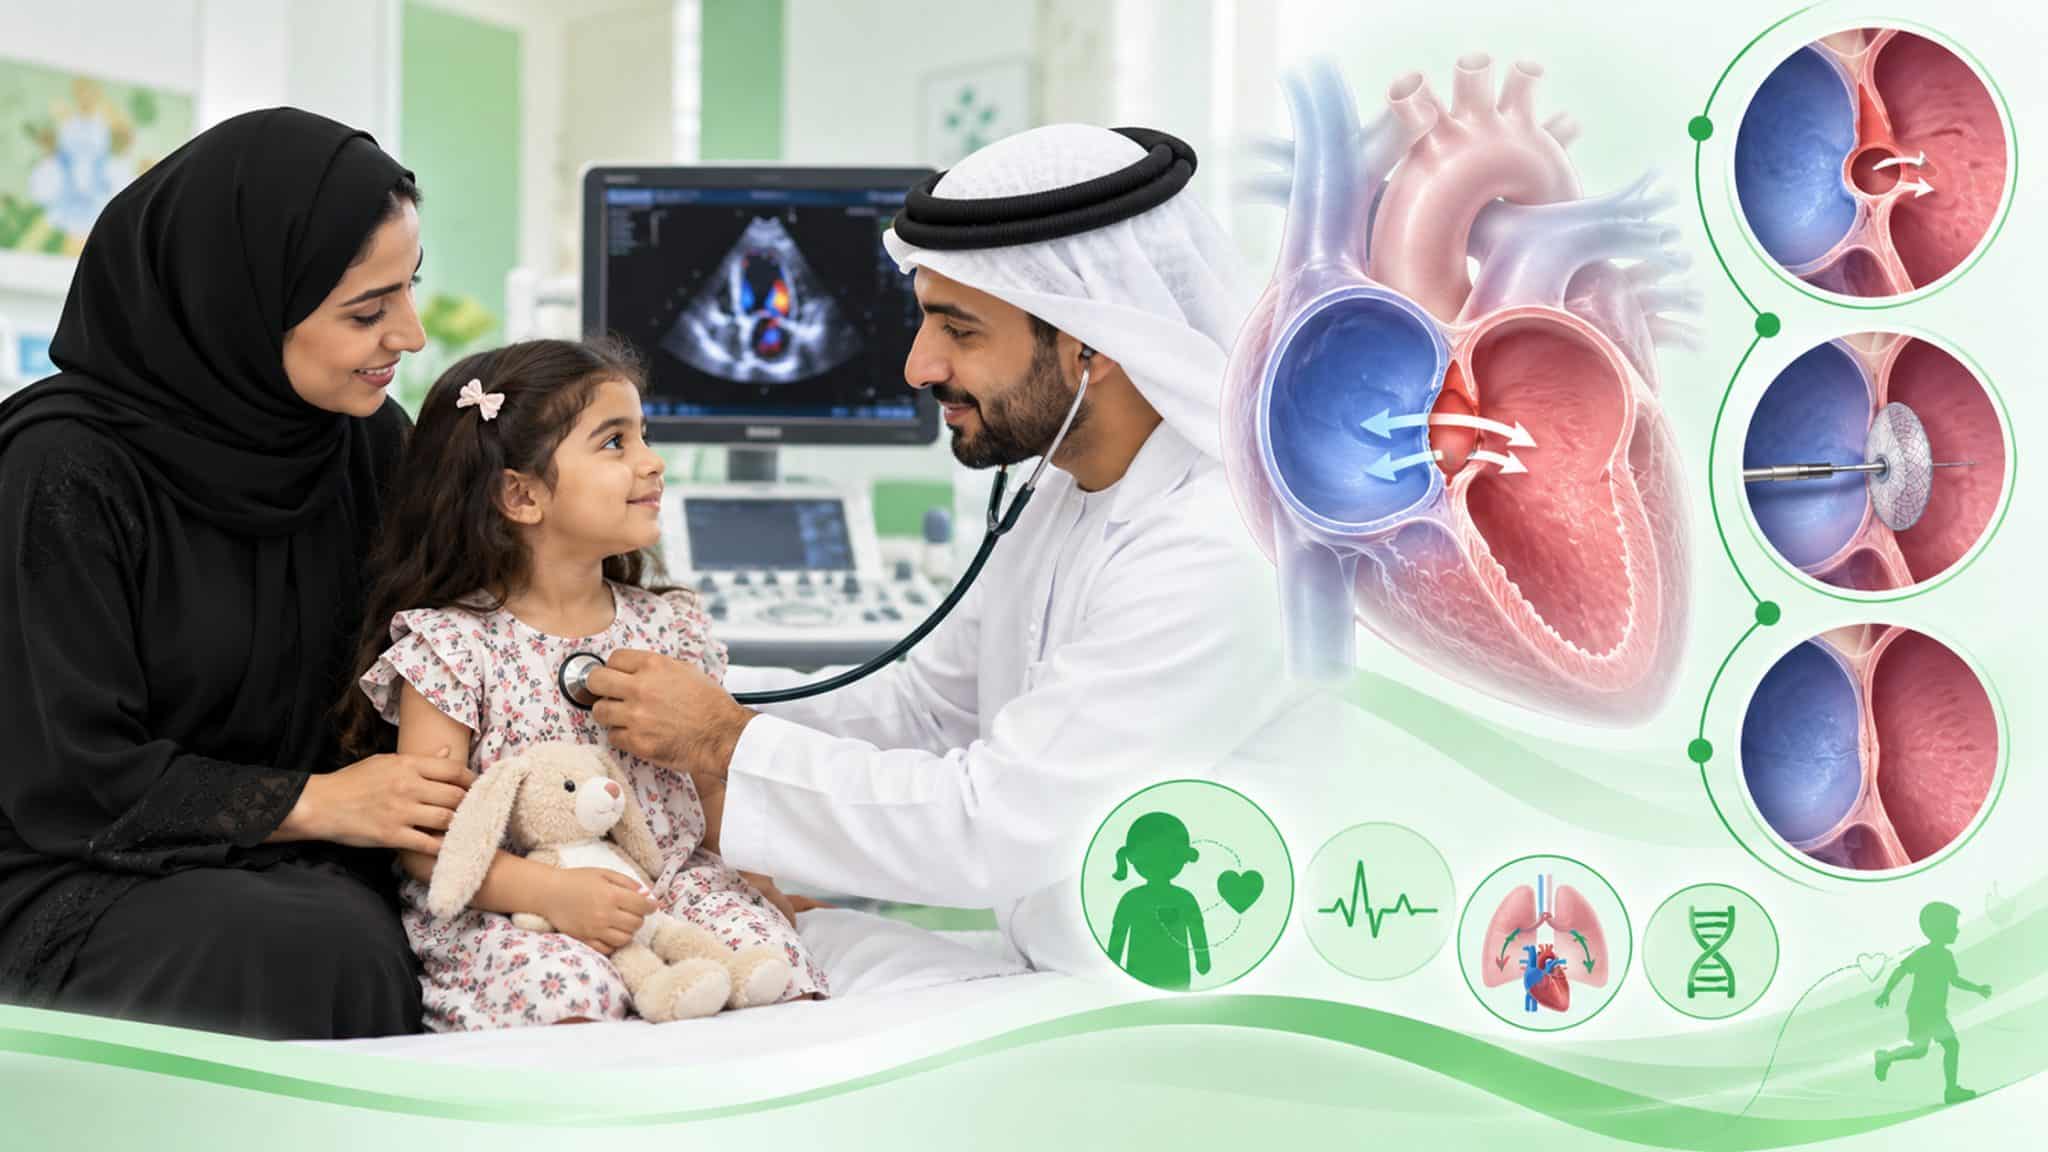
The school entry medical is supposed to be a formality. Height, weight, eyesight, vaccination record, a quick listen to the chest. Then the doctor moves the stethoscope a little higher, listens again, and asks whether anyone has ever mentioned a murmur.
Nobody has. The child is five, runs everywhere, and has barely needed a doctor since infancy. Two weeks later an echocardiogram shows a hole between the two upper chambers of her heart, and it has almost certainly been there since before she was born.
This is a common way for an atrial septal defect, or ASD, to come to light: quietly, late, and in a child who looks entirely well.
It is also one of the more reassuring diagnoses in pediatric cardiology, once a family understands what it is and what it isn’t. At KidsHeart, our Pediatric Cardiology team diagnoses and follows children with ASDs from our flagship Dubai Healthcare City branch, with the same care available in Abu Dhabi and Al Ain.
The Wall Between the Upper Chambers
The heart has four chambers. The two upper ones, the atria, receive blood as it returns: the right atrium from the body, the left atrium from the lungs. A thin wall of tissue called the atrial septum keeps the two apart. Our older post on how the normal heart works walks through this layout for parents who want the full picture.
An ASD is a gap in that wall. Because pressure on the left side of the heart is slightly higher, some oxygen-rich blood slips across from the left atrium to the right and takes an extra lap through the lungs. The right side of the heart ends up handling more blood than it was built for.
A small gap barely changes anything. A large one, over years, can stretch the right side of the heart and raise pressure in the blood vessels of the lungs.
ASDs are common. According to Stanford Medicine Children’s Health, they account for about 10% to 15% of congenital heart disease. Most occur by chance, with no clear cause. They are seen more often in girls.
A small number of ASDs are linked to a genetic condition, such as Down syndrome or Holt-Oram syndrome, which also affects the bones of the arms and hands, and occasionally ASDs run in families. When a parent or sibling has had one, a cardiologist may suggest an echocardiogram for other children in the family, even if they seem perfectly well.
Doctors describe ASDs by location. The most common, a secundum ASD, sits in the middle of the wall and is the type most likely to shrink or close with time. Others, such as primum and sinus venosus defects, sit near the valves or the large veins, never close on their own, and usually need surgery.
Not the Same as a PFO
Every baby is born with a small flap-like opening between the atria called the foramen ovale. Before birth it lets blood bypass the lungs, and in most children it seals shortly after delivery. When it stays partly open, it is called a patent foramen ovale, or PFO.
A PFO is not an ASD. No tissue is missing; the flap simply hasn’t fused. PFOs are extremely common, are often noted in passing on a newborn echocardiogram, and in children almost never need treatment.
Parents sometimes see “PFO” and “ASD” used loosely, even in conversation between professionals. Ask which one the report actually says, because the follow-up for each is very different.
This comes up often with newborns. Many babies in Dubai and elsewhere have an echocardiogram in the first days of life for an unrelated reason, and the report mentions a small opening at the atrial level. In a healthy newborn that is most often a PFO or a tiny secundum ASD, and the usual plan is a single repeat scan months later to confirm it has closed or shrunk.
A Hole That Rarely Announces Itself
Unlike a large ventricular septal defect, which often causes symptoms in the first weeks of life, an ASD usually produces none in early childhood. The pressure difference between the upper chambers is small, so the murmur is soft and easy to miss in a crying baby.
What doctors listen for is a subtle change in the heart sounds themselves, alongside a gentle murmur, often picked up only when a calm older child sits still for a proper exam. That is why so many ASDs are found at a preschool or school entry check rather than at birth.
An electrocardiogram (ECG) may show signs that the right side of the heart is working harder, and a chest X-ray may show it slightly enlarged. The echocardiogram is what confirms the diagnosis, showing the size and position of the gap and how much blood is crossing it. For families in Dubai, this can all happen in a single visit at Dubai Healthcare City.
When a large ASD does cause symptoms, they tend to be quiet ones: tiring more easily than friends, frequent chest infections, or slow weight gain.
Small Enough to Watch, Large Enough to Close
Many secundum ASDs found in infancy shrink or close by themselves within the first couple of years. A small defect in a child with a normal-sized heart is usually just watched with occasional echocardiograms.
Watching is not a waiting room. In the meantime, the child goes to nursery, plays sports, travels, and has vaccinations on the usual schedule. The echocardiogram every year or so is simply checking two things: whether the gap is getting smaller, and whether the right side of the heart is staying a normal size. If both answers stay reassuring, the plan stays the same.
The decision to close one rests on several findings together:
- The size of the defect and whether it is getting smaller
- Whether the right side of the heart is enlarged
- The type and location of the defect
- Symptoms such as tiring easily or poor growth
- The child’s age, since many cardiologists aim to close a significant ASD before or around school age
No single number settles it. Two children with defects of similar size can end up with different plans if one heart is showing strain and the other isn’t.
Closing a significant ASD in childhood matters because the effects of the extra blood flow build slowly. Adults whose ASD was never found can develop pulmonary hypertension, heart rhythm problems, or right-sided heart failure decades later, which is exactly what early closure is meant to prevent.
A Device Instead of an Incision
For most secundum ASDs that need closing, the first option is a catheter-based device closure. A thin tube is guided from a vein in the groin up into the heart, and a small double-disc device is opened on either side of the gap to seal it. Over the following months, the heart’s own tissue grows over the device.
Children typically go home the next day, with no chest incision and a short recovery.
Before the procedure, the cardiology team usually repeats the echocardiogram to measure the defect precisely and confirm there is enough tissue around its edges to hold a device. The procedure itself is done under general anesthesia or deep sedation, and parents can usually see their child soon afterward. Most children are back at school within a week, with a short break from rough play while the device settles.
Defects that are very large, have an unsuitable rim of tissue, or sit in the wrong position for a device, including primum and sinus venosus types, are repaired with open-heart surgery, where the surgeon closes the gap with stitches or a patch. The outcomes of both approaches in children are excellent.
Life After Closure
Most children who have an ASD closed in childhood go on to live without restrictions, including full participation in school sports once their cardiologist clears them. Follow-up is lighter than many parents expect: an echocardiogram and ECG at set intervals in the first year or so to confirm the device or patch is secure and the right side of the heart has settled back to normal size. Some children are advised to take antibiotics before certain dental procedures for a period after closure. Once the first year’s scans look settled, many children move to checkups every few years, and some are discharged from routine follow-up altogether.
Our post-surgical follow-up plans set out how those reviews are scheduled after both device closure and surgery. They can take place at Dubai Healthcare City, at our Al Karamah or MBZ branches in Abu Dhabi, or in Al Ain.
The five-year-old at the school medical didn’t have a problem that started that week. She had a quiet one that had simply never been heard. Finding it at five, before the right side of her heart had taken years of extra work, is close to the best timing there is. For families in Dubai whose child has just been told about a murmur at a school or nursery check, booking a cardiology assessment is how that soft sound gets a proper explanation.

Dr. Mohamed Sulaiman
Consultant, Fetal & Pediatric Cardiologist – American Board Assistant professor, Columbia University, New York

Dr. Emile A. Bacha
Pediatric Cardiac Surgeon – American Board